Disorders of Pigmentation

On this page

Melanocyte & Melanin - The Colour Code

  • Melanocytes:
    • Origin: Neural crest cells.
    • Location: Epidermal basal layer (ratio ~1:10 keratinocytes), hair matrix, uvea, inner ear.
    • Function: Synthesizes melanin within melanosomes.
  • Melanin Synthesis:
    • Key enzyme: Tyrosinase (copper-dependent).
    • Pathway: $L-Tyrosine \xrightarrow{Tyrosinase} L-DOPA \xrightarrow{Tyrosinase} Dopaquinone \rightarrow Melanins$.
    • Types: Eumelanin (brown/black), Pheomelanin (yellow/red, cysteine-rich).
  • Melanosomes: Lysosome-related organelles for melanin synthesis, storage, transfer to keratinocytes.
  • Skin Color: Determined by melanocyte activity, melanosome type/size/distribution, degradation rate; not melanocyte number.
  • Regulation: UV radiation, MSH, ACTH stimulate melanogenesis.
Loading diagram…
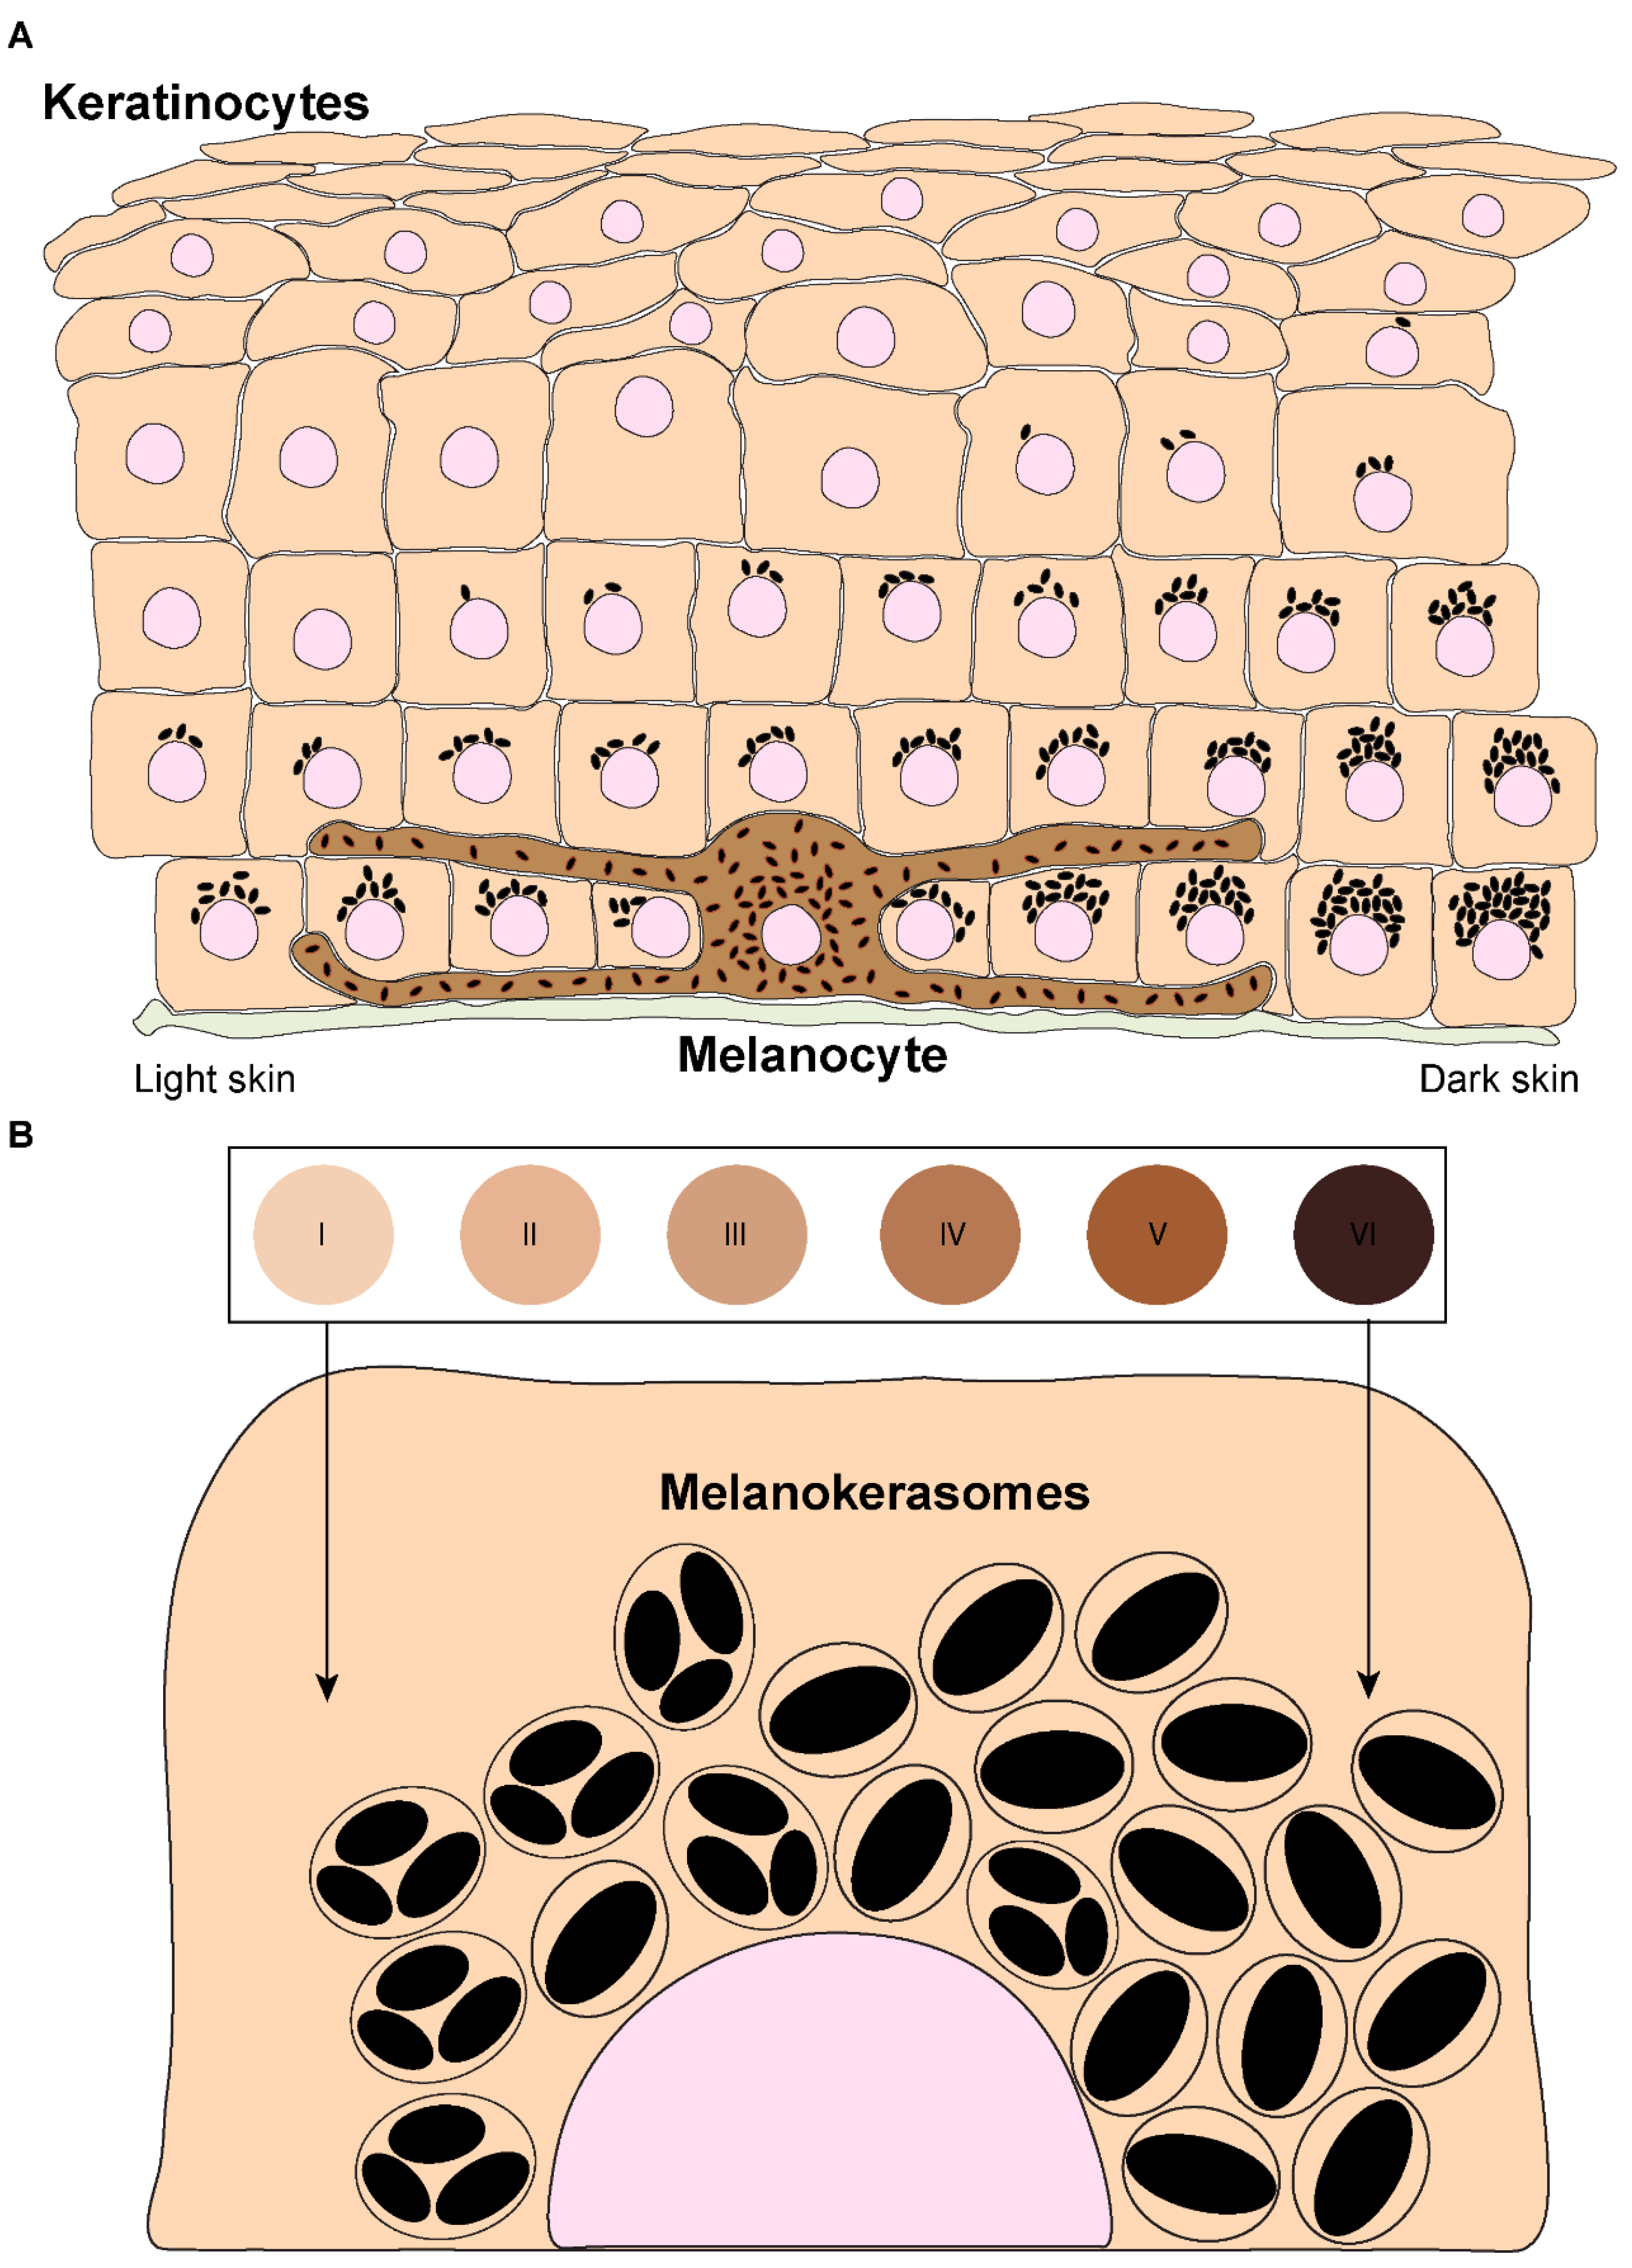
![Melanocyte transferring melanosomes to keratinocytes](https://ylbwdadhbcjolwylidja.supabase.co/storage/v1/object/public/notes/L1/Pathology_Dermatopathology_Disorders_of_Pigmentation/8c79d9b9-2471-42b1-a349-914cee7a1ff1.png)
> ⭐ Oculocutaneous albinism Type 1 (OCA1): *TYR* gene mutations cause deficient tyrosinase activity, reducing melanin.

Hypopigmentation - When Colour Fades

FeatureVitiligoAlbinism (OCA)Piebaldism
EtiologyAutoimmune melanocyte destruction; genetic factorsGenetic defect, melanin synthesis (TYR gene)Autosomal dominant; KIT gene; melanoblast migration defect
ClinicalAcquired, progressive patches; Koebner +veCongenital hypopigmentation (skin, hair, eyes); nystagmus, photophobiaCongenital white forelock (poliosis); stable, symmetrical midline patches
HistologyMelanocytes absent; T-cell infiltrateMelanocytes present; melanin ↓/absentMelanocytes absent in depigmented areas
Key DxWood's lamp (chalky white); autoimmune screen (thyroid)Ocular signs (nystagmus); family Hx; genetic testStable since birth; characteristic distribution; family Hx +ve

Hyperpigmentation - The Darker Side

  • Increased melanin production or deposition.
FeatureMelasmaPost-Inflammatory Hyperpigmentation (PIH)Lentigines (Solar/Senile)Ephelides (Freckles)
EtiologyHormonal (pregnancy, OCPs), UV exposurePost-inflammatory (acne, eczema)Chronic UV exposure, agingGenetic, UV exposure
ClinicalSymmetrical, irregular, brownish macules/patches on sun-exposed areas (face)Macules/patches at site of prior inflammationWell-demarcated, brown macules/patches on sun-exposed areasSmall, light brown macules, darken with sun
Histology↑ Melanin in epidermis ± dermis (melanophages); normal melanocyte count↑ Melanin in epidermis ± dermis (melanophages); variable melanocyte count↑ Melanin in basal layer, elongated rete ridges, normal/↑ melanocytes↑ Melanin in basal keratinocytes, normal melanocyte count

⭐ Riehl's melanosis is a pigmented contact dermatitis, often seen on the face and neck, presenting as diffuse greyish-brown hyperpigmentation. It's a form of PIH.

  • Wood's lamp: Epidermal melasma is accentuated; dermal is not. (📌 Epidermal Enhanced)
  • Lentigo maligna: A melanoma in situ, presents as an enlarging, irregular pigmented macule on sun-damaged skin, especially in elderly individuals. Requires biopsy for diagnosis.

Nevi & Melanoma - Moles & Red Flags

Benign melanocytic nevi (moles) are common. Malignant melanoma is a deadly skin cancer; early detection is key.

Nevus TypeLocationKey Features
JunctionalEpidermisFlat, dark; nests at D-E jct.
CompoundEpidermis/DermisRaised, pigmented; nests epi & dermis
IntradermalDermisDome-shaped, flesh/light brown; older adults
Blue NevusDermisBlue-black; spindle cells, Tyndall effect
Spitz NevusChildren (often)Pink/red papule; histologically mimics melanoma

📌 ABCDE Criteria for Melanoma Detection:

  • Asymmetry: One half unlike the other.
  • Border: Irregular, scalloped, or poorly defined.
  • Color: Varied (shades of tan, brown, black; may include red, white, blue).
  • Diameter: Usually > 6 mm (pencil eraser size).
  • Evolving: Change in size, shape, color, elevation, or new symptom (e.g., bleeding, itching, crusting).

⭐ Acral lentiginous melanoma is the most common type in dark-skinned individuals, often found on palms, soles, or under nails (subungual).

High‑Yield Points - ⚡ Biggest Takeaways

  • Vitiligo: Autoimmune melanocyte destruction causes depigmented patches; Koebner phenomenon often positive.
  • Albinism: Genetic tyrosinase deficiency (e.g., OCA1) impairs melanin synthesis; normal melanocyte count.
  • Melasma: Hormonally-influenced hyperpigmentation, typically on sun-exposed facial areas; exacerbated by UV.
  • Acanthosis Nigricans: Velvety, hyperpigmented plaques in flexures; signals insulin resistance or internal malignancy.
  • Lentigo Solaris: Benign "age spots" from chronic sun exposure; characterized by ↑ melanocyte number.
  • Café-au-lait Macules: Multiple large macules are a diagnostic criterion for Neurofibromatosis Type 1 (NF1).

Unlock the full lesson and continue reading

Signup to continue reading this lesson and unlimited access questions, flashcards, AI notes, and more

Scan to download app

Scan to download
UNLOCK FREE ACCESS

Practice Questions: Disorders of Pigmentation

  1. 1. Which malignancy most commonly arises in a chronic non-healing ulcer (Marjolin ulcer)?

    • A. Squamous carcinoma
    • B. Basal cell carcinoma
    • C. Kaposi sarcoma
    • D. Malignant melanoma
    Show answer

    Answer: A. Squamous carcinoma

    Squamous carcinoma - Squamous carcinoma classically develops in chronic non-healing ulcers, burn scars, chronic osteomyelitis sinuses, and venous stasis ulcers as a Marjolin ulcer. - Persistent inflammation, tissue damage, and cellular turnover promote keratinocyte mutations; these tumors may be more aggressive and have greater metastatic potential than typical UV-induced lesions. Basal cell carcinoma - Basal cell carcinoma is primarily associated with cumulative ultraviolet exposure, especially on sun-exposed areas such as the face, rather than transformation of chronic ulcers. - Although it is the most common skin cancer, BCC rarely arises in chronic ulcers or scars, making it less characteristic than SCC in this setting. Kaposi sarcoma - Kaposi sarcoma is a vascular tumor associated with HHV-8, particularly in immunocompromised patients, rather than a carcinoma arising from chronic tissue damage. - It typically presents as purplish cutaneous or mucosal nodules, not as malignant transformation of a long-standing ulcer. Malignant melanoma - Malignant melanoma arises from melanocytes, commonly in association with intense intermittent ultraviolet exposure or pre-existing nevi, rather than chronic ulcers. - Its melanocytic origin distinguishes it from Marjolin ulcer, the characteristic SCC developing in a chronic scar or non-healing wound.

  2. 2. Which of the following conditions is depicted?

    • A. Plexiform neurofibroma
    • B. Lymphatic malformation
    • C. Lipoma
    • D. Venous malformation
    Show answer

    Answer: A. Plexiform neurofibroma

    Plexiform neurofibroma - A plexiform neurofibroma produces a diffuse, infiltrating soft-tissue mass along nerve distributions, classically described as a “bag of worms” on palpation. - The rope-like, tortuous subcutaneous masses reflect intertwined nerve-associated tissue and are characteristic of neurofibromatosis type 1. Venous malformation - Venous malformation consists of abnormally dilated venous channels, typically producing a soft, compressible, bluish swelling. - The depicted rope-like soft-tissue overgrowth is more consistent with an infiltrative nerve-associated lesion than dilated venous channels. Lymphatic malformation - Lymphatic malformation consists of abnormal lymphatic spaces and may present as a cystic swelling or clusters of superficial vesicles. - These lymphatic spaces differ from the intertwined nerve-associated tissue producing the depicted rope-like soft-tissue masses. Lipoma - Lipoma is a localized mass of mature adipose tissue, typically presenting as a soft, circumscribed subcutaneous swelling. - A localized adipose mass does not account for the diffuse, rope-like, infiltrative pattern of the depicted nerve-associated lesion.

  3. 3. Serotonin is also known as?

    • A. 3-Methoxytyramine
    • B. Tryptamine
    • C. 2-Phenylethan-1-amine
    • D. 5-hydroxytryptamine
    Show answer

    Answer: D. 5-hydroxytryptamine

    5-hydroxytryptamine - Serotonin is the common name for 5-hydroxytryptamine (5-HT), a neurotransmitter derived from tryptophan. - The name reflects a hydroxyl group at position 5 of the indole ring and an ethylamine side chain. 3-Methoxytyramine - 3-Methoxytyramine is a metabolite of dopamine, produced through catechol-O-methyltransferase activity rather than representing serotonin. - Its association with dopamine metabolism distinguishes it from serotonin, whose chemical name is 5-hydroxytryptamine. Tryptamine - Tryptamine is an indoleethylamine derived from tryptophan but lacks serotonin’s hydroxyl group at position 5. 2-Phenylethan-1-amine - 2-Phenylethan-1-amine is a naturally occurring trace amine that can act as a neuromodulator or neurotransmitter. - Although structurally related to some recreational drugs, it is not serotonin, whose established synonym is 5-hydroxytryptamine.

  4. 4. Which of the following is NOT a standard clinical association of the tongue finding shown in the photograph?

    • A. Psoriasis
    • B. Melkersson-Rosenthal syndrome
    • C. Myasthenia gravis
    • D. Down syndrome
    Show answer

    Answer: C. Myasthenia gravis

    Myasthenia gravis is the exception: it produces fatigable muscle weakness, sometimes involving bulbar muscles, and is not a standard association of fissured tongue. The photograph shows branching dorsal grooves characteristic of fissured tongue. Down syndrome and Psoriasis are recognised associations. Melkersson-Rosenthal syndrome classically combines fissured tongue, recurrent facial palsy, and orofacial swelling.

  5. 5. Patient with pigmented skin lesion shows pagetoid spread of atypical melanocytes. Diagnosis?

    • A. Lentigo maligna (melanoma in situ)
    • B. Superficial spreading melanoma
    • C. Blue nevus
    • D. Nodular melanoma
    Show answer

    Answer: B. Superficial spreading melanoma

    Superficial spreading melanoma - Superficial spreading melanoma characteristically shows a radial growth phase, with atypical melanocytes spreading along the dermo-epidermal junction and into the epidermis. - Upward migration of atypical melanocytes into the spinous and granular layers is pagetoid spread, a hallmark histological feature supporting this diagnosis. Lentigo maligna (melanoma in situ) - Lentigo maligna (melanoma in situ) usually arises on chronically sun-damaged skin of older individuals, especially the face, with atypical melanocytes predominantly confined to the basal layer. - Although it has a radial growth phase, prominent upward pagetoid spread into the epidermis is not the typical distinguishing feature compared with superficial spreading melanoma. Nodular melanoma - Nodular melanoma is characterized by an aggressive vertical growth phase, with rapid downward expansion into the dermis rather than a prominent radial phase. - It typically presents as a dark, raised nodule and lacks the prominent pagetoid spread associated with superficial spreading melanoma. Blue nevus - Blue nevus is a benign melanocytic lesion composed of dermal melanocytes containing melanin deep within the dermis, producing a blue or blue-gray appearance. - Because its melanocytes are dermal rather than epidermal, it does not show atypia with upward pagetoid spread into the epidermis.

  6. 6. All of the following are true statements about malignant melanoma EXCEPT:

    • A. Prognostic relevance of Clark's level of invasion
    • B. Acral survival better than superficial spreading
    • C. Limb perfusion for treatment of in-transit metastases
    • D. Better overall survival in women compared with men
    Show answer

    Answer: B. Acral survival better than superficial spreading

    Acral survival better than superficial spreading - Acral lentiginous melanoma generally has a poorer prognosis than superficial spreading melanoma because it often occurs in concealed sites and is diagnosed at a more advanced stage. - Superficial spreading melanoma typically remains in the radial growth phase longer before deep invasion, so it generally has a better prognosis; therefore this statement is false. Prognostic relevance of Clark's level of invasion - Clark’s classification is a valid prognostic tool based on the anatomical level of melanoma invasion through the epidermis and dermis, graded from levels I to V. - Although Breslow depth is now the most important prognostic measure, Clark’s level remains a recognized prognostic factor and therefore this statement is true. Limb perfusion for treatment of in-transit metastases - Isolated limb perfusion is a recognized local treatment for melanoma metastases confined to an extremity, particularly recurrent or in-transit disease. - Perfusion delivers agents such as melphalan regionally, making this statement true for appropriately localized limb melanoma. Better overall survival in women compared with men - Women generally have better survival from malignant melanoma than men, partly because lesion distribution and biological factors may contribute to more favorable outcomes. - Women more often develop lesions on the lower limbs, whereas men more frequently have trunk lesions; therefore this statement is true.

  7. 7. A 35-year-old woman has a six-month history of photosensitive erythema over both cheeks and the nose, sparing the nasolabial folds, with focal scalp alopecia. Which autoimmune disease is most likely?

    • A. Rheumatoid arthritis
    • B. Dermatomyositis
    • C. Systemic lupus erythematosus
    • D. Progressive systemic sclerosis
    Show answer

    Answer: C. Systemic lupus erythematosus

    Systemic lupus erythematosus - Systemic lupus erythematosus classically causes a photosensitive malar rash involving the cheeks and nose while sparing the nasolabial folds. - Additional cutaneous lupus manifestations, including focal alopecia, support SLE as the most likely diagnosis. Rheumatoid arthritis - Rheumatoid arthritis is primarily a chronic inflammatory joint disease and does not typically cause a photosensitive malar rash with nasolabial-fold sparing. - Although rheumatoid nodules and other cutaneous findings may occur, they do not explain the prominent facial rash and focal alopecia described here. Dermatomyositis - Dermatomyositis may cause photosensitive rashes, but typical distinguishing findings include a heliotrope rash around the eyes and Gottron papules over bony prominences. - The described malar rash with nasolabial-fold sparing and alopecia are more characteristic of systemic lupus erythematosus. Progressive systemic sclerosis - Progressive systemic sclerosis typically produces progressive skin thickening and hardening, often affecting the extremities and face rather than an erythematous photosensitive rash. - The patient's malar distribution and focal alopecia are not typical manifestations of systemic sclerosis.

  8. 8. A 60-year-old woman has oral burning aggravated by spicy food. Examination reveals lace-like white oral lesions with focal erosions. Which histological feature is characteristic?

    • A. Flattened rete ridges
    • B. Sawtooth rete ridges
    • C. Elongated rete ridges
    • D. Bulbous rete ridges
    Show answer

    Answer: B. Sawtooth rete ridges

    Sawtooth rete ridges are characteristic of lichen planus, suggested here by lace-like white oral lesions and symptomatic erosions. Its histology typically includes basal-cell degeneration and a band-like lymphocytic infiltrate beneath the epithelium. Flattened rete ridges may accompany epithelial atrophy but are not the characteristic pattern requested. Elongated rete ridges are nonspecific and occur in conditions such as psoriasis and chronic epithelial hyperplasia. Bulbous rete ridges may occur in epithelial dysplasia or reactive hyperplasia rather than representing the classic lichen planus pattern.

  9. 9. An adolescent boy develops coarse terminal hairs and acne within a 15-cm hyperpigmented patch during puberty. What is the most likely diagnosis?

    • A. Becker nevus
    • B. Sebaceous nevus
    • C. Melanocytic nevus
    • D. Sebaceous adenoma
    Show answer

    Answer: A. Becker nevus

    Becker nevus - A Becker nevus is a large hyperpigmented patch that commonly appears during adolescence in males, often on the shoulder or upper trunk. - Its androgen sensitivity produces characteristic hypertrichosis, increased coarseness, and acne within the lesion, particularly during puberty. Melanocytic nevus - Melanocytic nevus can be pigmented and hairy, and benign nevi may thicken or become more conspicuous during puberty. However, a large hyperpigmented patch developing coarse hair and acne in an adolescent male is more characteristic of Becker nevus. Sebaceous adenoma - A sebaceous adenoma is usually a small flesh-colored to yellowish papule or nodule, commonly occurring on the face. - It does not typically form a broad hyperpigmented macule with progressive hair growth and acne during adolescence. Sebaceous nevus - A sebaceous nevus is usually a congenital yellowish-orange, waxy, or bumpy lesion, most often located on the scalp or face. - It does not typically present as a large, flat hyperpigmented macule that develops hair and acne during adolescence; later changes may include verrucosity or tumors.

  10. 10. A characteristic sweaty-feet odour is associated with which disorder?

    • A. Multiple carboxylase deficiency
    • B. Phenylketonuria
    • C. Tyrosinemia
    • D. Isovaleric Acidaemia
    Show answer

    Answer: D. Isovaleric Acidaemia

    Isovaleric Acidaemia causes a characteristic sweaty-feet odour from isovaleric acid accumulation and results from isovaleryl-CoA dehydrogenase deficiency. Multiple carboxylase deficiency affects several biotin-dependent enzymes and may produce a cat-urine odour rather than the classic sweaty-feet odour. Phenylketonuria produces a musty or mousy odour rather than a sweaty-feet odour. Tyrosinemia is classically associated with a boiled-cabbage odour rather than the sweaty-feet odour specified here.

Flashcards: Disorders of Pigmentation

  1. 1. Simple lentigo occurs due to an increase in  at dermal-epidermal junction.

    Show answer

    melanocytes

  2. 2. Neurotization of nevus occurs due to progressive loss of _____ activity and acquisition of _____ activity in deeper nervelike nevus cells

    Show answer

    tyrosinase · cholinesterase

  3. 3. In diabetic dermopathy, histology shows hyperpigmentation of _____ layer of epidermis along with deposition of _____ and _____ in the dermis

    Show answer

    basal · haemosiderin · melanin

  4. 4. Melanocytic nevi (moles) are common benign neoplasms caused by acquired activating mutations in components of the signaling pathway.

    Show answer

    RAS

  5. 5. method is the most specific method for staining melanin and stains it brown black

    Show answer

    Dihydroxyphenylalanine (DOPA)-oxidase

  6. 6. Neurotization of nevus suggests nature of nevus

    Show answer

    benign (benign/malignant)

  7. 7. Pigmentation in acanthosis nigricans is due to

    Show answer

    hyperkeratosis

  8. 8. What type of nevus shows lymphocytic infiltration surrounding nevus cells? _____

    Show answer

    Halo nevus

  9. 9. _____ has a characteristic histopathology of "Claw clutching a Ball' appearance

    Show answer

    Lichen nitidus

  10. 10. _____ giant cells are lipid-containing macrophages, having a central ring of nuclei while the peripheral cytoplasm is clear due to accumulated lipid

    Show answer

    Touton

Everything you need for Indian Medical PG prep

Get full Oncourse access with lessons, practice questions, flashcards and AI study tools.

GET STARTED FOR FREE
75% OFFLimited time offer
GET 75% OFF